August 24, 2026
By Dr. Alex Ong, Optometrist, FAAO, FOWNS, CPNP & Richie Huang, Optometrist, FOWNS, CPNP

Photo generated with AI
Myopia management has evolved significantly over the past decade. Much of the current discussion focuses on orthokeratology, atropine and specialized spectacle lenses, all of which have contributed substantially to the advancement of childhood myopia care.1,2
However, in many parts of Asia and several other regions, soft contact lenses have also become an important option for managing childhood myopia. Their availability provides clinicians and families with an additional treatment modality that may better align with visual demands, lifestyle considerations, parental preferences and treatment goals. While numerous clinical studies have demonstrated the efficacy of soft contact lenses in slowing myopia progression and axial elongation, less attention is often given to how these lenses perform in everyday clinical practice. Clinical trials provide important evidence, but real-world outcomes may be influenced by factors such as compliance, visual demands, outdoor exposure, lifestyle habits and patient acceptance.
The following cases illustrate how soft contact lens-based myopia management can be incorporated into routine clinical care and how the outcomes compare with contemporary treatment expectations.
Case Series
Two children attending regular myopia management reviews were fitted with soft myopia management contact lenses following discussions with their families regarding progression and treatment options.
Patient ‘LYH’
The first patient, LYH, demonstrated continued myopia progression while wearing single-vision spectacles, with axial length increasing from 22.89 mm to 23.32 mm over a 12-month period, representing 0.43 mm of axial elongation. Following this progression, a comprehensive discussion was held with the parents regarding the available myopia management options, including low-dose atropine, orthokeratology, soft daily disposable myopia management contact lenses and peripheral defocus spectacle lenses.
Although low-dose atropine was considered, the parents were reluctant to pursue this option because it would require consultation with an ophthalmologist, they had concerns about potential medication-related side effects, and they understood that atropine would still need to be combined with spectacles or contact lenses to correct the child’s refractive error. Orthokeratology was also discussed; however, the parents were concerned about LYH’s ability to handle overnight lenses and maintain adequate lens hygiene. After considering the benefits and limitations of each approach, they elected to proceed with a soft daily disposable myopia management contact lens.
LYH was subsequently fitted with a senofilcon A daily disposable contact lens incorporating RingBoost technology. With consistent lens wear of approximately six days per week, axial length increased by only 0.11 mm during the following 12 months, representing a substantial reduction in axial elongation compared with the preceding year in single-vision spectacles.
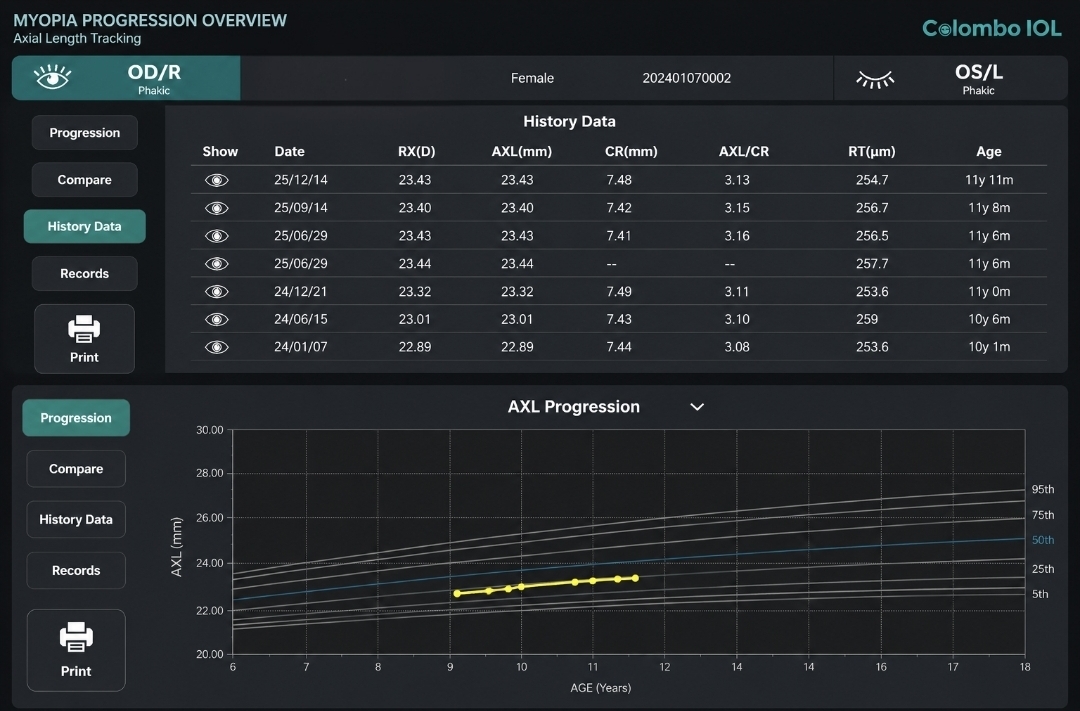
Figure 1: Chart showing LYH axial length progression
Compared with the patient’s pre-treatment growth rate, this represented a reduction of approximately 74% in annual axial elongation. More importantly, the observed growth of 0.11 mm per year fell within the range increasingly considered a favorable treatment outcome in contemporary myopia management.1,2
Patient ‘XYN’
The second patient, YXN, had previously been managed with a myopia control spectacle lens. The family subsequently expressed interest in contact lenses to provide greater visual freedom and convenience. Both orthokeratology and soft daily disposable myopia management contact lenses were discussed as treatment options. Although the potential benefits and safety profile of orthokeratology were explained, the parents remained hesitant because their understanding of contact lens wear was that lenses should not be worn during sleep. Despite counseling on the evidence supporting the safe use of orthokeratology with appropriate patient selection, fitting and follow-up, they preferred to begin with a daytime soft contact lens. The parents felt this would allow both themselves and YXN to become familiar with contact lens handling and wear before considering overnight orthokeratology in the future.
An initial trial with a concentric-ring soft myopia management lens design achieved an acceptable clinical fit. However, the patient reported subjective shadowing and reduced visual quality, despite no obvious fitting abnormalities being observed during the assessment.
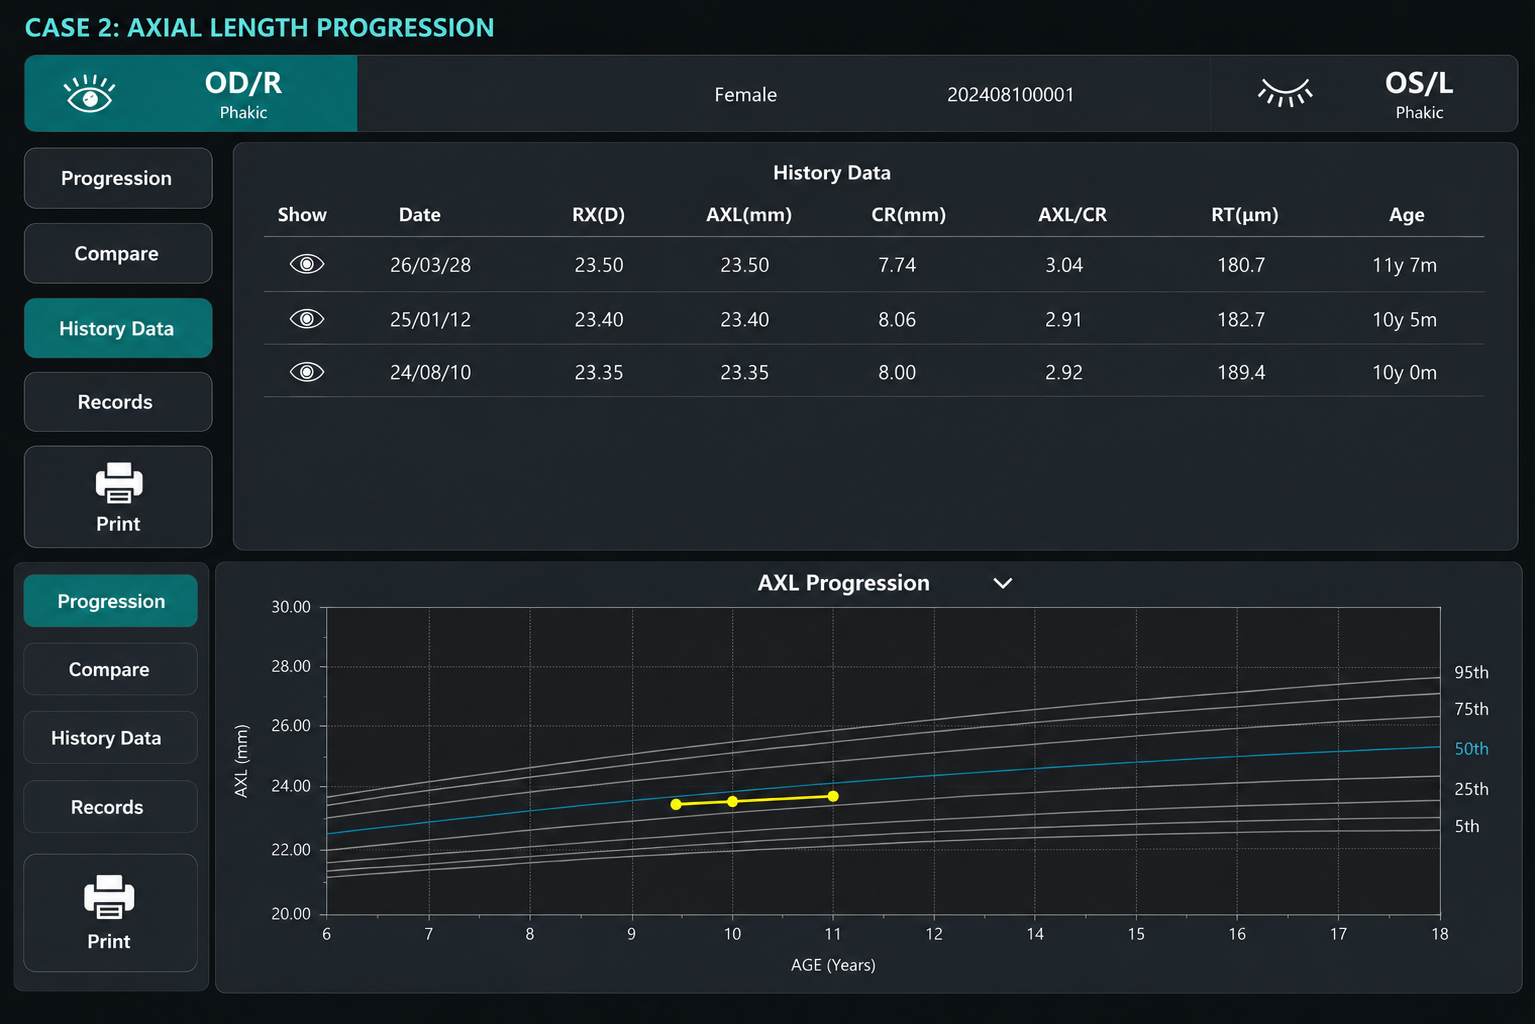
Figure 2: Chart showing YXN axial length progression
The patient was subsequently fitted with etafilcon A with extended depth of focus (EDOF) design. The lenses demonstrated good centration, improved visual clarity and excellent comfort. Over approximately 19 months of follow-up, axial length increased from 23.35 mm to 23.50 mm, representing only 0.15 mm of growth. When annualized, this corresponded to approximately 0.10 mm of axial elongation per year, again comparing favourably with treatment targets commonly used in clinical practice.1,2
Although these cases represent different clinical scenarios, both demonstrated favourable outcomes and highlighted the importance of selecting a lens design that provides not only treatment efficacy but also acceptable visual quality and long-term patient acceptance.
Discussion
How Do These Results Compare With Clinical Trials?
One of the challenges in translating research into clinical practice is that real-world outcomes do not always mirror those reported in randomized clinical trials. Children differ in compliance, visual habits, near work behavior, outdoor exposure and follow-up attendance.
Nevertheless, the outcomes observed in these two cases compare favourably with findings from major myopia management studies.
The MiSight 1-day trial reported significantly slower axial elongation and myopia progression over six years compared with single-vision controls.¹ Similarly, studies investigating multifocal and EDOF soft contact lens designs have demonstrated meaningful reductions in axial elongation compared with conventional correction methods.2,5
While direct comparisons should be interpreted cautiously, both cases achieved annualized axial elongation rates of approximately 0.10–0.11 mm per year. These values are substantially lower than the 0.30–0.40 mm per year commonly observed in progressing untreated myopic children and compare favorably with contemporary treatment goals.1,2
Increasingly, clinicians are shifting their focus away from refractive change alone and toward the rate of ocular growth. In practical terms, many clinicians aim for annual axial elongation rates below 0.20 mm in school-aged children, with even lower targets for older children. The outcomes observed in both cases fall comfortably within these treatment expectations.
One Lens Design Does Not Fit Every Child
Another important lesson from the presented cases is that no single optical design is ideal for every patient.
The two lens designs used in these cases represent different optical approaches to myopia management. Both approaches seek to modify retinal image quality in a manner that slows excessive ocular growth, although the visual experience may differ between individual patients.1,2,5
In the second case, a concentric-ring design produced subjective shadowing despite an acceptable lens fit, whereas the EDOF design provided improved visual quality and long-term acceptance. This observation is consistent with what many clinicians experience in practice. Treatment success depends not only on efficacy but also on visual quality, comfort, adaptation and compliance.
For this reason, it is beneficial for clinicians to have access to more than one evidence-based myopia management-specific soft contact lens design. The goal is not to identify the best lens for every child, but rather the most suitable lens for the individual patient sitting in front of us.
Building Upon Established Contact Lens Practice
An equally important observation is that myopia management soft contact lenses build upon clinical skills that many practitioners already utilize in routine contact lens care.
The optical design may be new, but many of the skills required for successful fitting are not. Lens assessment, over-refraction, visual performance evaluation, patient education, compliance monitoring and follow-up have long been part of conventional contact lens practice.
Optometrists have traditionally been responsible for fitting and managing soft contact lenses in children and teenagers. The introduction of myopia management soft contact lenses builds upon these established competencies rather than replacing them with an entirely new skill set.
While the treatment objective has evolved from refractive correction alone to also addressing excessive ocular growth, the fundamental principles of successful contact lens fitting remain unchanged.
Monitoring Myopia in the Real World
The presented cases also highlight the value of monitoring axial length alongside refractive status.
The International Myopia Institute recommends that clinicians consider both refractive error and axial length when monitoring treatment effectiveness because axial length provides direct information regarding structural eye growth and treatment response.²
Cycloplegic refraction remains the gold standard for determining refractive error in children and continues to play an important role during diagnosis, baseline assessment and when accommodative anomalies are suspected.² However, real-world clinical practice may not always mirror ideal research protocols. In many practices, clinicians integrate visual acuity, retinoscopy, subjective refraction, binocular vision findings, patient symptoms, contact lens performance and axial length measurements when determining treatment response and deciding whether cycloplegic assessment is required.
The question may therefore be less about choosing between cycloplegic refraction and axial length monitoring and more about understanding when each provides clinically meaningful information. While cycloplegia remains an important tool, successful myopia management ultimately depends on combining multiple sources of clinical information to guide patient care.
Conclusion
The two cases presented demonstrate that successful soft contact lens-based myopia management depends on more than optical design alone. Lens fit, visual quality, patient acceptance, compliance and ongoing monitoring all contribute to treatment outcomes.
Perhaps more importantly, the outcomes achieved in these patients compare favourably with contemporary treatment expectations and reinforce the value of monitoring ocular growth alongside refractive status.
For many practitioners, myopia management soft contact lenses represent a natural evolution of existing contact lens practice, combining established fitting skills with evidence-based strategies aimed at slowing excessive ocular growth and supporting long-term ocular health.
 |
Dr. Alex Ong, Doctor of Optometry, FAAO, FOWNS, CPNP (US)
|
 |
Mr. Richie Huang, B.Sc Optom, FOWNS, CPNP (US)Optometrist, TaiwanMr. Huang is a practicing optometrist and founder of JD Optometry Group in Taiwan. He is also the current President of the New Taipei City Optometrists Association, and was the Past President of the Taiwan Optometrists Association (TOA). He specializes in elderly vision care and children’s vision development, combining clinical expertise with a strong commitment to professional education. As a Certified Personalized Nutrition Practitioner with the American Nutrition Association and members and Fellows of OWNS, his work covers within visual nutrition, paediatric myopia management, binocular vision and geriatric vision care, with strong engagement in public education and professional training. His passion for optometry is reflected in his ongoing contributions to public awareness and his leadership in advancing eye care standards across Taiwan. |
References
- Chamberlain P, Peixoto-de-Matos SC, Logan NS, Ngo C, Jones D, Young G. A 6-Year Clinical Trial of MiSight 1 Day Contact Lenses for Myopia Control. Optom Vis Sci. 2022;99(3):204-212.
- Sankaridurg P, Tahhan N, Kandel H, et al. IMI Clinical Management Guidelines Report. Invest Ophthalmol Vis Sci. 2023;64(6):3.
- Bullimore MA. The Safety of Soft Contact Lenses in Children. Optom Vis Sci. 2017;94(6):638-646.
- Wolffsohn JS, Flitcroft DI, Gifford KL, et al. IMI Overview and Introduction Reports. Invest Ophthalmol Vis Sci. 2019;60:M1-M19.
- Shen EP, Chu HS, Cheng HC, Tsai TH. Center-for-Near Extended Depth-of-Focus Soft Contact Lens for Myopia Control in Children. Ophthalmol Ther. 2022;11:1577-1588.
Read more about myopia control soft contact lenses here